Rolling admission · Istanbul · Delivered in English
Head & Neck Surgery Observership the tumour board, oncological resection and reconstruction in Istanbul
Follow how a university ear, nose and throat department stages head and neck cancer, agrees treatment at its weekly tumour board and carries out resection and reconstruction, with no operative role, on the lists scheduled during your dates.
What can an observer follow in Head & Neck Surgery?
What you see depends on the department's clinical calendar during your placement; the list below describes the department's usual scope, not a guaranteed programme.
The weekly head and neck tumour board: how imaging, endoscopy and pathology are brought together and how treatment is agreed
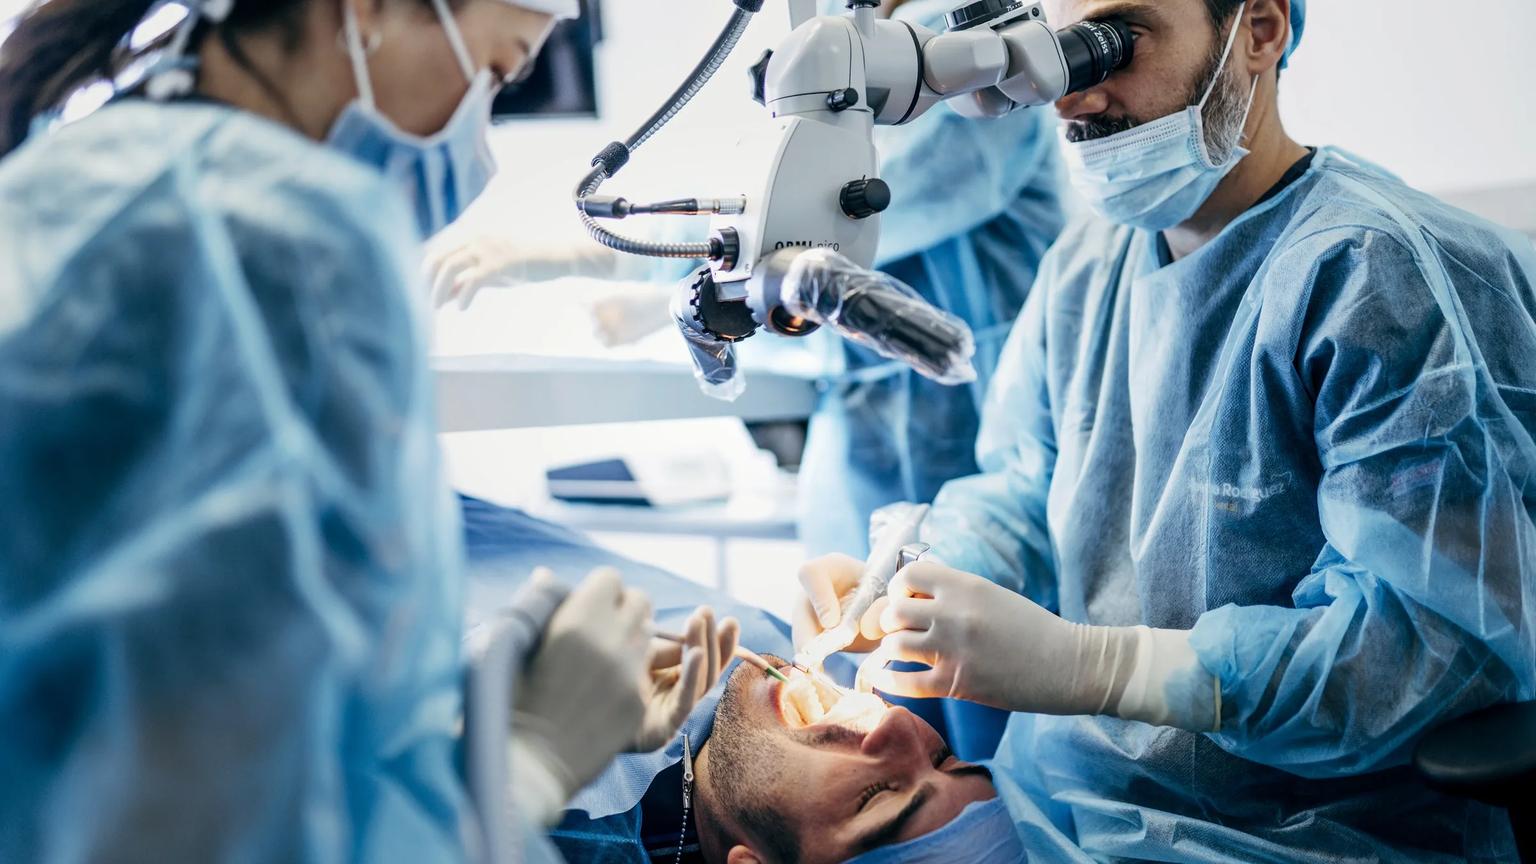
Head and neck oncology lists: resection and reconstruction, where scheduled
Assessment in the outpatient clinic and endoscopy room: examination of the neck, endoscopy of the upper airway and the work-up of a neck lump
Microlaryngoscopy and airway assessment, where laryngeal disease is examined or treated endoscopically
Reconstruction planning with the plastic surgery team for larger defects, where such cases are listed
Neck dissection as part of an oncological resection, where scheduled, and the reasoning behind its extent
Post-operative care on the ward: airway, swallowing and voice review, and the plan for follow-up
How is head and neck cancer treatment decided, and who shapes the decision?
Treatment starts with an accurate map of the disease. The patient is examined in the clinic, the upper airway is inspected endoscopically, a tissue diagnosis is obtained and cross-sectional imaging defines the extent of the primary tumour and the state of the neck. Together these give the stage. General health, nutrition, dental status and the patient's own priorities, particularly speech and swallowing, are recorded at the same time, because they affect which treatments are realistic.
The plan is then agreed at the tumour board, where surgeons, oncologists, radiologists and pathologists review each case together. Early disease is often treated with a single modality, either surgery or radiotherapy, while more advanced disease usually needs combined treatment. The choice between them depends on the site, the stage, the expected effect on function and the patient's fitness and wishes. For some tumours of the larynx and throat, the central question is whether the organ can be preserved without compromising cure.
When surgery is chosen, three decisions travel together: how the tumour will be removed with clear margins, how the neck will be managed and how the defect will be reconstructed. Larger reconstructions are planned with the plastic surgery team, and the airway plan is agreed with the anaesthetist before the day. After the operation, recovery of speech and swallowing and the schedule of surveillance matter as much as the wound. An observer who follows a case from the tumour board to the ward sees how these decisions connect.
How this page differs
This page covers head and neck oncology within the ear, nose and throat department. Otology and cochlear implantation have their own focus page. Thyroid and parathyroid surgery are followed in the thyroid and endocrine surgery placement, and free-flap reconstruction is covered in depth on the reconstructive microsurgery page.
Who applies, and which route fits?
Clinical Observership
Trainees and graduate physicians in otorhinolaryngology or surgery who want to see how a tumour board works and how its decisions are carried into theatre; clinical-year students are eligible but usually gain more from the wider department.
Clinical Fellowship
Otorhinolaryngologists with a specialist qualification who state head and neck oncology as their interest within the department; the department decides allocation, and oncological lists are followed alongside its other clinics and lists.
What an observer does not do
Both routes are strictly observational: observers attend theatre and clinic without patient contact, do not scrub or assist, and are not assessed on any procedure.
Strictly observational: no scrubbing, assisting or endoscopy, and no part in examination or consent.
Oncological operations can run through the day; you follow from the place the theatre team assigns and may be asked to step out at times.
Major resections are not scheduled every week; no number or type of case, including free-flap reconstruction, can be promised.
No procedural certification, logbook entries or competence sign-off: the certificate records attendance or completion, not operative experience.
The two routes at a glance
The two routes side by side
Clinical Observership
Clinical Fellowship
Duration
1, 2 or 4 weeks (extension possible on request)
12 to 24 months, agreed with the host department
Who it is for
Medical students in clinical years and graduate physicians from outside Turkey
Recognised specialists and family physicians seeking advanced exposure beyond standard specialty training
Extended observational attachment to one department: daily practice, service structure and specific techniques
Certificate
Certificate of attendance issued by the host hospital and signed by its Medical Director
Certificate on completion issued under the accreditation of the affiliated university school of medicine
Start
Rotations typically begin on a Monday; dates are agreed individually
Start date planned around the date you request and the department's capacity
Before you apply
The programme is delivered in English and every applicant evidences their level with an official document.
Fees and terms are confirmed in writing after the eligibility review; they are not published on this page.
Apply three to six months ahead: departments accept only one or two observers at a time and files are reviewed in order.
State your focus in the objectives of your application. Allocation follows the department's lists during your dates.
What do candidates ask about Head & Neck Surgery?
Is this a head and neck fellowship with operating experience?
No. The Clinical Fellowship is an extended observational attachment of twelve to twenty-four months to the ear, nose and throat department, with head and neck oncology stated as your interest. Neither route includes operating or assisting, and no cases can be logged. The host hospital issues a certificate that records the attachment; it is not a subspecialty qualification.
How often are major resections scheduled?
The tumour board meets weekly, but the operating lists depend on the patients referred and on theatre and intensive care capacity, so the number and type of major cases in any week cannot be promised. Clinics, endoscopy sessions and ward rounds fill the other days. A placement of four weeks gives a wider view than one week, but no particular operation can be promised.
Does the placement include thyroid surgery?
Thyroid and parathyroid surgery belong to the thyroid and endocrine surgery placement, which has its own page. A placement is with one department for its whole duration, so choose the department that matches your main interest and state it in your objectives.
Can maxillofacial or plastic surgeons apply?
The Clinical Observership is open to medical students in their clinical years and to graduate physicians from outside Turkey. The Clinical Fellowship requires a recognised specialist qualification, and the fellowship focus published for this department is written for otorhinolaryngologists. Plastic surgeons interested in reconstruction should also read the reconstructive microsurgery page. If your primary degree is in dentistry, write to hello@atdera.com before applying so that eligibility can be confirmed with the host department.
What background helps me follow the tumour board?
The programme does not publish a minimum level of experience. In practice the discussion is easier to follow if you know the anatomy of the upper airway and the levels of the neck, the outline of tumour staging and the basics of reading head and neck imaging. Fluent spoken English matters, because board discussions move quickly.
Apply for an observership with Head & Neck Surgery as your focus
One online application for both routes. State Head & Neck Surgery as your focus in your objectives; ATDERA reviews the file and prepares it for the ENT department, then replies with next steps, typically within two working days.
Five short steps: your details, education, programme choice, documents and declaration.
A personal link by email, so you can leave and return where you stopped — for 60 days.
Documents are uploaded in step 4; you need nothing to hand to begin.
ATDERA Global Limited (Companies House No. 17173428, registered in England and Wales) coordinates this programme for a university teaching hospital in Istanbul. ATDERA is not a hospital and does not provide clinical care; admission decisions and certificates are the host hospital's.
Ready to apply?
One online application covers both routes and all twenty-one specialties — details, programme choice and documents in five short steps. ATDERA reviews the file and replies with next steps, typically within two working days.